

< View All Healthcare Value Hub Articles
Georgia Survey Respondents Receive Unexpected Medical Bills, Incur Medical Debt, and Express Bipartisan Support Government Action
Download Report

 Georgia Medical Debt Brief
Executive Summary

Background
In the absence of affordable care options, individuals may find themselves burdened by medical costs. In 2024, nearly 100 million Americans owed over $220 billion in medical debt.[1] Medical debt is largely driven by unaffordable bills: many Americans with private coverage must pay thousands of dollars in out-of-pocket expenses to get care, including increasingly high premiums, deductibles, co-insurance, and copayments.[2],[3],[4] This lack of affordability is reflected in national survey findings showing that many medical debts stem from one-time or short-term medical expenses that are often unexpected,[5] and that roughly half of adults say they could not pay a $500 unexpected medical bill, and would either have to incur debt to pay it or would not be able to pay the bill at all.[6] These factors negatively impact long-term financial security and ability to afford care in the future.
The aim of this brief is to present findings from the Georgia CHESS survey on unexpected medical bills, financial burdens due to medical costs, medical debt, and support for policy solutions. Detailed information on the survey methods, sampling approach, and study population is provided in the Appendix.
Unexpected Medical Bills
Thirty percent (30%) of Georgia respondents received an unexpected medical bill in the past year. Among respondents who received an unexpected bill, experiences varied by coverage. Respondents with employer-sponsored and Georgia Medicaid most frequently reported an unexpected medical bill (35% and 34%, respectively), followed by respondents enrolled in individually purchased insurance (e.g., through the health care Marketplace (32%) and Medicare (18%).
Financial Burdens Due to Medical Cost
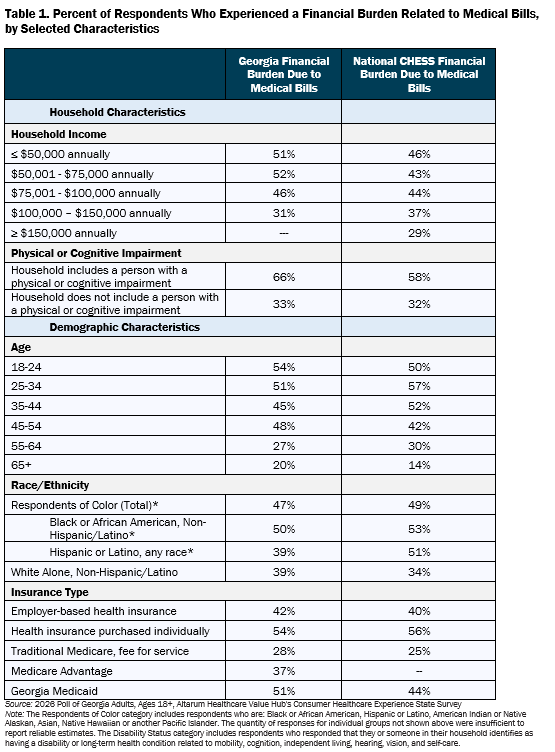
Nearly half of Georgia respondents (43%) reported experiencing at least one financial burden due to medical costs in the last year.
Financial burdens were not evenly distributed across the population. Higher rates of medical cost-related burden were reported among younger adults, respondents of color, respondents with a disability or who live with a person with a disability, and respondents with Medicaid. The findings in Georgia are consistent with what we see across the National CHESS data set regarding the impact of financial burdens from medical costs (Table 1).
Respondents reported a range of strategies and consequences when trying to manage medical expenses. 18% reported being contacted by a collection agency, 14% reported using up all or most of their savings, and 13% reported borrowing money or taking out a loan or another mortgage on their home. Fewer respondents reported going without basic necessities like food, heat or housing due to medical bills (12%), accumulating large amounts of credit card debt (11%), or being placed on a long-term payment plan (10%).
Medical Debt and Health Insurance
Thirty-three percent (33%) of Georgia respondents reported that they or a family member currently have outstanding medical bills (Table 2). Among respondents with medical debt, the most reported amount was $1,000-$2,499 (20%), followed by less than $500 (19%), $2,500 – $4,999 (18%), $500 – $999 (17%) and $5,000 – $7,499 (10%). Still, 1 in 10 respondents (10%) report owing over $10,000 in medical debt.
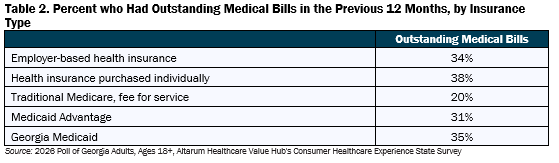
Medical debt frequently occurred despite insurance coverage. Respondents with medical debt (34%) reported having health insurance at the time they incurred the debt, and nearly three in four respondents (74%) had no gaps in coverage in the past 12 months. At the time of the survey, 4 in 10 (40%) reported being covered by employer-sponsored insurance, followed by insurance bought on the Marketplace exchange (15%), Medicare Advantage (13%), Traditional Medicare, (9%) and Georgia Medicaid (8%). Medical debt affects both insured and uninsured respondents (Table 2).
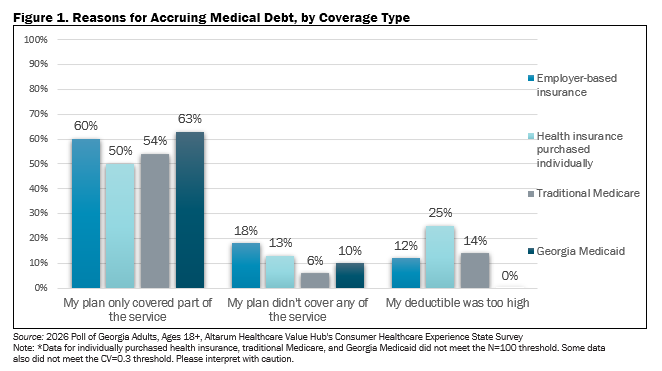
Respondents identified multiple reasons for incurring medical debt, reflecting differences in insurance coverage (Figure 1). Over half of Georgia respondents reported that their insurance only covered half of the service (58%), followed by insurance not covering the service at all (15%). In lesser numbers, respondents reported their deductible was too high to meet (12%), and 4% reported that their coinsurance was too high.
Respondents most frequently identified hospital services (65%) and laboratory services (lab tests, x-rays, scans) (32%), as the source of their medical debt.
Other commonly reported sources included doctor or technician services in the hospital (28%), doctor or technician services not in hospital (25%), and urgent care centers (19%). Smaller proportions cited physical therapy or pain management services (10%), dental services (10%), mental healthcare or addiction treatment (8%), and pregnancy-related expenses (5%), and as the source of their medical debt.

Differences in Amount and Reasons for Medical Debt
While insurance coverage plays a central role in how medical debt occurs, the prevalence and severity of medical debt also vary across income, age, disability status, and race and ethnicity.
Income
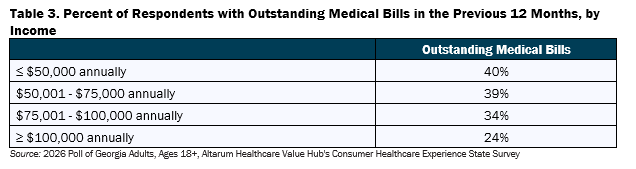
Medical debt was reported across income levels, though both the likelihood of having medical debt and the amounts owed varied by household income (Table 3). Among respondents with a household income below $50,0000, over 6 in 10 (62%) reported having $2,500 or less in medical debt, while 13% owe more than $10,000 versus those with a household income above $100,000 (57% and 10% respectively).*
*Data for some income groups did not meet the N=100 threshold.
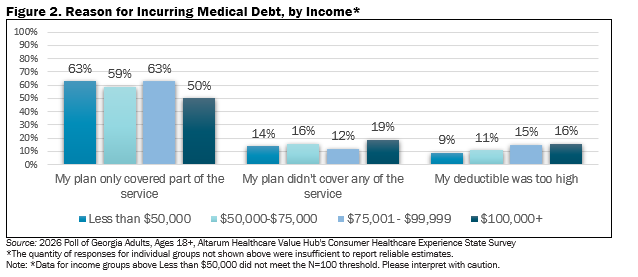
Differences were also observed in the reasons respondents reported for incurring medical debt. While respondents across income groups cited similar reasons overall (Figure 2), lower ‑income respondents more frequently reported incurring medical debt because services were only partially covered by insurance (63%), whereas respondents in higher income brackets more often cited high deductibles as a contributing factor (16%).
Age
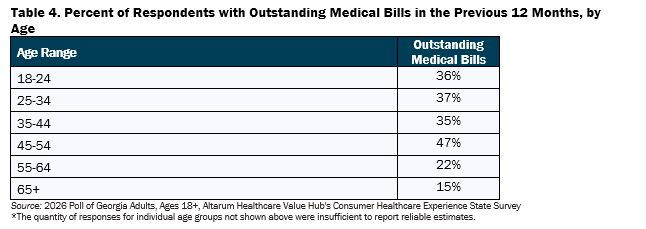
Medical debt prevalence varied by age (Table 4). Respondents ages 45-54 reported the highest rates of medical debt (47%), followed by those ages 25-34 (37%) and 18-24 (36%). In contrast, those ages 65+ reported lower rates of medical debt (15%). Across all age groups, respondents most often reported lower amounts of medical debt, although a smaller share in each age group reported owing $10,000 or more.
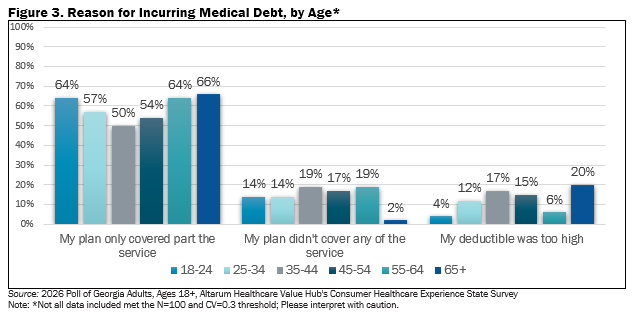
Reasons for incurring medical debt were generally similar across age groups, though the relative importance of specific factors varied (Figure 3). More than half of respondents aged 65+ (66%) and 55-64 (64%) report incurring medical debt because their insurance plan didn’t fully cover the service(s) they received. Higher rates of medical debt due to high deductibles were reported among respondents ages 65+ (20%), while respondents aged 35-44 and 55-64 reported higher rates of their plans not covering any of their needed services (both 19%).
Disability
Some of the highest rates of medical debt were seen among households that include a person with a disability. Respondents whose households included a member with a disability reported higher rates of medical debt for themselves or their family (48%) compared to those without a disabled household member (27%). Respondents with a household member with a disability most frequently reported owing between $2,500 – $4,499 in medical debt (21%), while those without a household member with a disability most frequently reported medical debt of less than $500 (22%).
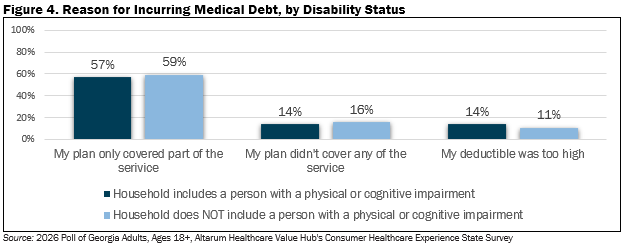
Reasons for incurring medical debt were similar among respondents with or without a household member with a disability. Compared with respondents without a disabled household member, respondents with a household member with a disability reported similar rates of medical debt due to non-covered services (14% vs 16%), plans partially covering the service (57% vs 59%), and deductibles (14% vs 11%) (Figure 4).
Race and Ethnicity
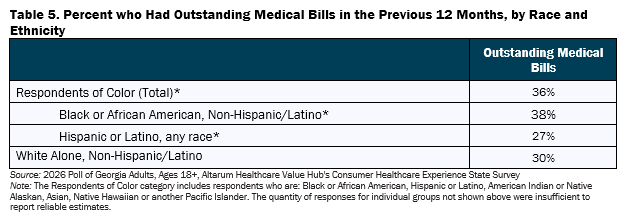
Differences in medical debt exposure were also seen across racial/ethnic groups (Table 5). Respondents of color reported higher rates of medical debt (37%) compared to White alone non-Hispanic respondents (30%). Black/African American respondents more commonly report owing less than $2,500 in medical debt (65%), followed by respondents of color respondents (63%) and white alone non-Hispanic respondents (50%).

Support for Solutions Across Party Lines
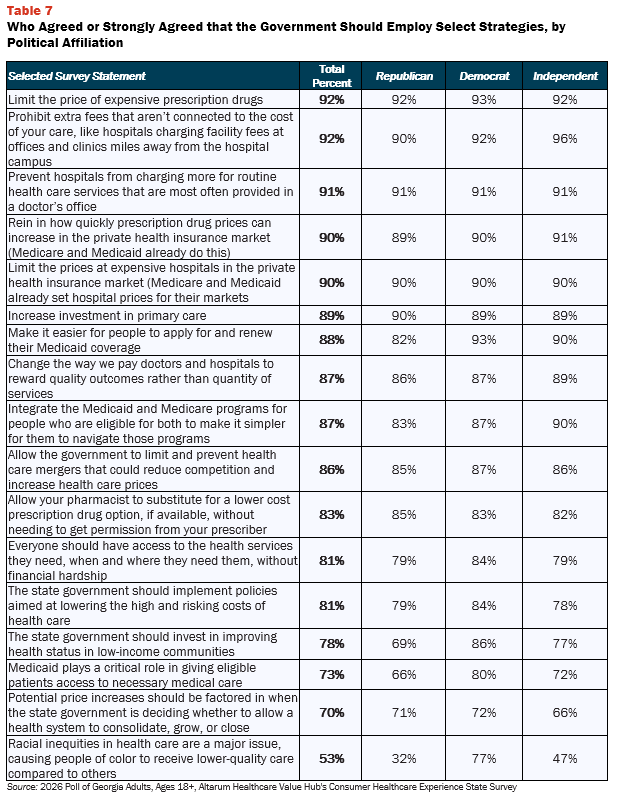
Support for addressing medical debt extended across political affiliations, with respondents expressing strong support for policy approaches aimed at reducing out‑of‑pocket costs, increasing price transparency, and preventing unexpected medical bills (Table 7).
Taken together, these findings indicate that medical debt is widely viewed as a shared affordability challenge and that there is broad public support for policy efforts to prevent medical debt before it occurs.


Conclusion
Findings from the Georgia Consumer Healthcare Experience State Survey show that unexpected medical bills, financial strain, and medical debt are common experiences for Georgia residents. Many respondents reported significant financial burdens related to medical costs, including using savings, taking on credit card debt, or carrying unpaid medical bills.
Medical debt was most often driven by unaffordable out-of-pocket costs, even among respondents with health insurance. Many respondents incurred medical debt because their insurance plan did not cover the service, or because their deductible or co-insurance was too high to afford. Differences in exposure to medical debt were observed across income, age, disability status, and race and ethnicity, underscoring that medical debt affects a wide range of Georgia households.
Respondents across the political spectrum expressed support for policies aimed at reducing out-of-pocket costs, increasing price transparency and preventing unexpected medical bills. Together, these findings highlight medical debt as a shared affordability challenge and point to broad public support for efforts to prevent medical debt before it occurs.
By grounding policy discussions in Georgia residents’ lived experiences, these findings can help state policymakers identify and evaluate strategies that protect consumers from unaffordable out-of-pocket costs and prevent medical debt. For more information on healthcare affordability in Georgia and strategies that survey respondents support, please see the Georgia Health Care Affordability Consumer Healthcare Experience State Survey.
Notes
[1] Bell, C. (2024, October 1). CFPB Takes Action to Protect Consumers from Illegal Medical Debt Collection Practices. CR Advocacy. https://advocacy.consumerreports.org/press_release/cfpb-takes-action-to-protect-consumers-from-illegal-medical-debt-collection-practices/
[2] State Health Access Data Assistance Center (SHADAC). (2025). Median medical out-of-pocket spending [Data set]. State Health Compare, University of Minnesota. https://statehealthcompare.shadac.org
[3] State Health Access Data Assistance Center (SHADAC). (2025). Average annual employer sponsored insurance premium [Data set]. State Health Compare, University of Minnesota. https://statehealthcompare.shadac.org
[4] State Health Access Data Assistance Center (SHADAC). (2025). Average annual employer sponsored insurance deductible [Data set]. State Health Compare, University of Minnesota. https://statehealthcompare.shadac.org
[5] Lopes, L., Kearney, A., Montero, A., Hamel, L., & Brodie, M. (2022, June 16). Health Care Debt in the U.S.: The broad consequences of medical and dental bills – main findings – 9957. KFF.
[6] Health Care Debt in the U.S., KFF, 2022.
[7] Rakshit, S., Rae, M., Claxton, G., Amin, K., & Cox, C. (2024, February 12). The Burden of Medical Debt in the United States. Peterson-KFF Health System Tracker. https://www.healthsystemtracker.org/brief/the-burden-of-medical-debt-in-the-united-states/#Share%20of%20adults%20who%20have%20medical%20debt,%20by%20demographics,%202021
[8] Young, G., Rae, M., Claxton, G., Wager, E., & Amin, K. (2022, March 10). How many people have enough money to afford private insurance cost sharing? Peterson-KFF Health System Tracker. https://www.healthsystemtracker.org/brief/many-households-do-not-have-enough-money-to-pay-cost-sharing-in-typical-private-health-plans/
[9] Elani, H. W., & Sommers, B. D. (2025). Fillings needed for gaps in government dental coverage. JAMA Health Forum, 6(2), e250370. https://doi.org/10.1001/jamahealthforum.2025.0370
[10] Ludomirsky, A. B., Schpero, W. L., Wallace, J., Lollo, A., Bernheim, S., Ross, J. S., & Ndumele, C. D. (2022). In Medicaid Managed Care Networks, Care Is Highly Concentrated Among A Small Percentage Of Physicians. Health Affairs, 41(5), 760–768. https://doi.org/10.1377/hlthaff.2021.01747
[11] Cottrill, A., Neuman, T., Lopez, L., & Hamel, L. (2024, July 26). What are the consequences of health care debt among older adults?. KFF. https://www.kff.org/medicare/issue-brief/what-are-the-consequences-of-health-care-debt-among-older-adults/
[12] Park, S., & Stimpson, J. P. (2024). Health care expenses and financial hardship among Medicare beneficiaries with functional disability. JAMA Network Open, 7(6), e2417300. https://doi.org/10.1001/jamanetworkopen.2024.17300
[13] Goodman, N., Morris, M., & Boston, K. (2017). Financial inequality: Disability, race and poverty in America. National Disability Institute. https://www.nationaldisabilityinstitute.org/wp-content/uploads/2019/02/disability-race-poverty-in-america.pdf
[14] Urban Institute. (2022). Communities of color disproportionally suffer from medical debt. https://www.urban.org/urban-wire/communities-color-disproportionally-suffer-medical-debt
[15] Zahnd, W. E., Hung, P., Crouch, E. L., Ranganathan, R., & Eberth, J. M. (2025). Health care access barriers among metropolitan and nonmetropolitan populations of eight geographically diverse states, 2018. The Journal of Rural Health, 41(1), e12855. https://doi.org/10.1111/jrh.12855
[16] Levey, N. N. (2022, January 16). 100 million people in America are saddled with health care debt. KFF Health News. https://kffhealthnews.org/news/article/diagnosis-debt-investigation-100-million-americans-hidden-medical-debt/

ppendix. Methodology and Population
Altarum’s Consumer Healthcare Experience State Survey (CHESS) is designed to elicit respondents’ views on a wide range of health system issues, including confidence using the health system, financial burden and possible policy solutions. This survey, conducted from July 8th to July 23rd, 2026, used a web panel from Dynata with a demographically balanced sample of nearly 1,400 respondents who live in Georgia. Information about Dynata’s recruitment and compensation methods can be found here. The survey was conducted in English or Spanish and restricted to adults ages 18 and older. Respondents who finished the survey in less than half the median time were excluded from the final sample, leaving 1,379 cases for analysis. After those exclusions, the demographic composition of respondents was as follows, although not all demographic information has complete response rates:
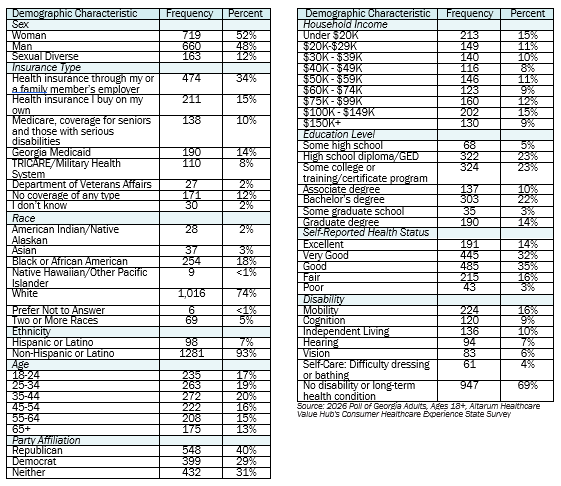
Percentages in the body of the brief are based on weighted values, while the data presented in the demographic table is unweighted. An explanation of weighted versus unweighted variables is available here. Altarum does not conduct statistical calculations on the significance of differences between groups in findings. Therefore, determinations that one group experienced a significantly different affordability burden than another should not be inferred. Rather, comparisons are for conversational purposes. The groups selected for this brief were selected by advocate partners in each state based on organizational/advocacy priorities. We do not report any estimates under N=100 and a co-efficient of variance more than 0.30.
Altarum in Action
Rhode Island Office of the Health Insurance Commissioner cites CHESS survey in letter to State House Committee on Health and Human Services about HB072 related to reimbursement rates and repealing affordability standards. Read more
Washington State Senator Patty Murray’s office cites the WA CHESS survey in press release about Senate Health, Education, Labor and Pensions (HELP) Committee hearing where Senator Murray questioned CEOs of major pharmaceutical companies about the high prices charged to Americans for their prescription drugs. Read more
Read More Altarum in Action Resources